

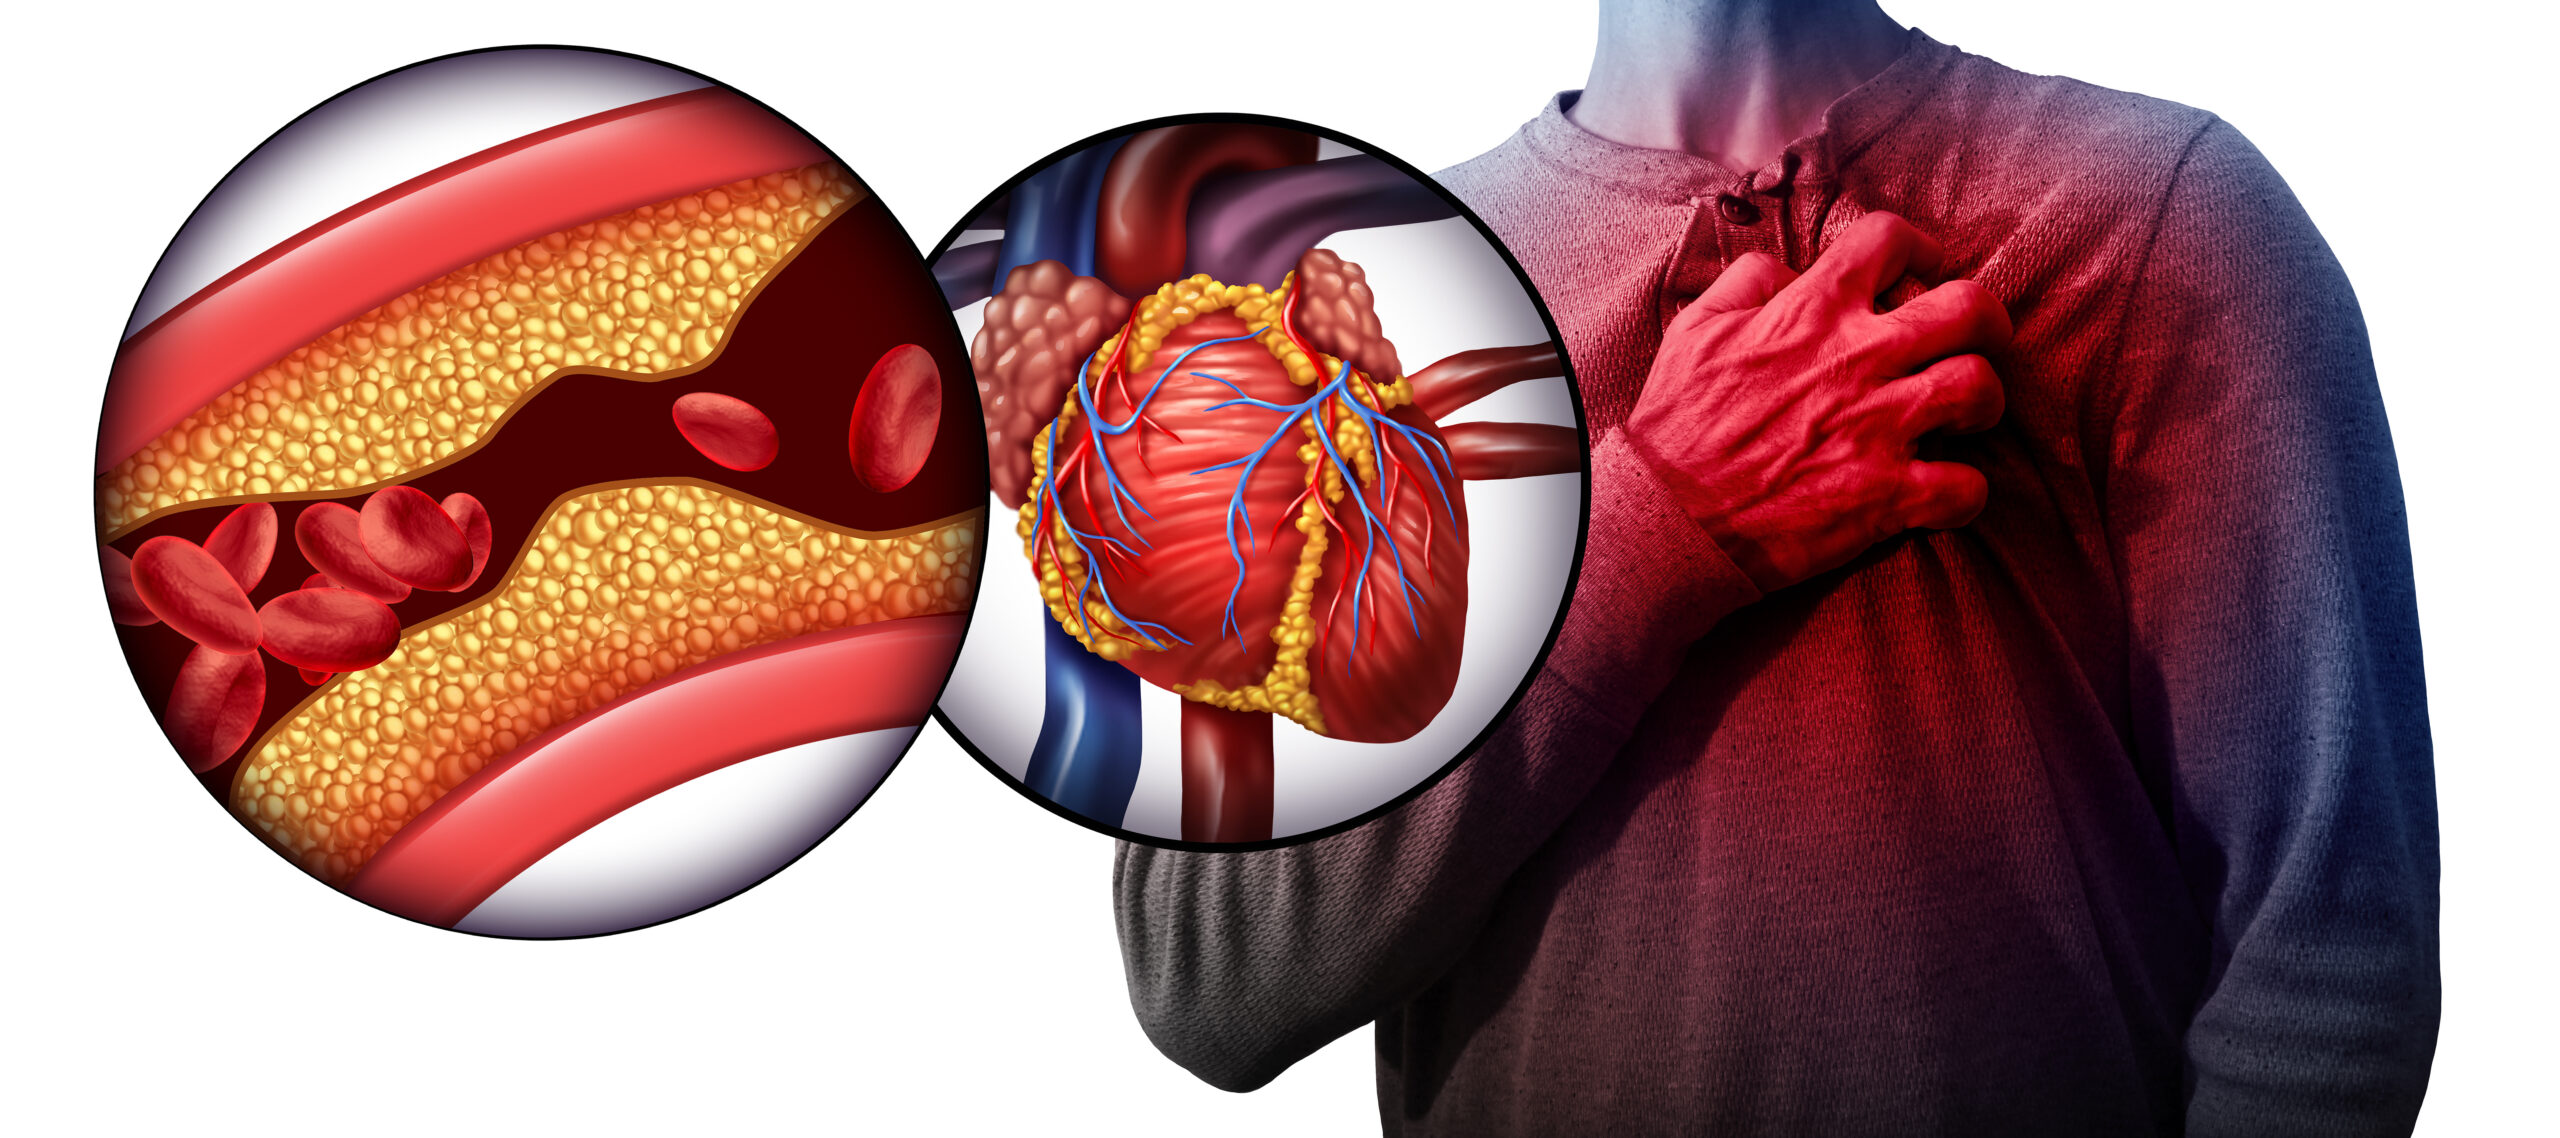
A “widowmaker” heart attack, more formally known as an anterior ST-segment elevation myocardial infarction (STEMI), is a frightening term for a type of heart attack that occurs when the main artery supplying blood to the heart becomes almost completely blocked.
It gets its name because it’s so severe that, without immediate treatment, it often proves fatal. This can be overwhelming to understand, but it’s important to know that with prompt medical care, widowmaker heart attack prognosis can be improved and lives can be saved.
How Serious Is a Widowmaker Heart Attack?
Widowmaker heart attack prognosis depends on how quickly one can get medical attention, since time is one of the most critical factors in survival. The 30-day mortality rate for a widowmaker heart attack is between 2.5 to 10%, with the mortality rate being slightly higher for women than men.
Unfortunately, many people who suffer from a heart attack do not know they’re at risk.
This was the same exact case for my client, who is a 40-year-old man who had a widowmaker heart attack while on a run. He had no past medical history and he participated avidly in CrossFit.
After his heart attack, he joined my 3-month VIP nutrition individual program and we worked closely together to optimize his nutrition to improve his cardiovascular function (his ejection fraction was 30% post-heart attack, indicating heart failure), improve his laboratory values (LDL was 138mg/dL and BP was 154/99mmHg), and reduce his risk of a future event.
In 3 months, he had increased his ejection fraction to 47%, his BP average was 117/76mmHg, and his cardiac rehab center asked him to be part of the testimonial advertisement because they have never seen such significant positive change in strength and recovery in such a short period.
My client attributed a lot of this to being nutrient-sufficient and addressing the underlying root cause with proper science-based nutrition.
I received an email from him 6 months after he completed the program, saying: “Hi Michelle, just an update. All doing great. My EF is now at 61% and all the readings are good. I’m also off of my beta blockers and statin. My bad cholesterol went from 138 to 28, it’s been amazing how my food intake has transformed it all. Thank you.”
Widowmaker Symptoms, Causes, and Risk Factors
What Are the Symptoms of a Widowmaker Heart Attack?
Widowmaker symptoms are similar to other heart attacks. A widowmaker heart attack can include one or more of the following symptoms:
- Pain or discomfort in the neck, jaw, back, arms, or stomach
- Shortness of breath
- Chest pain, tightness, or discomfort
- Lightheadedness, weakness, or feeling faint
- Breaking out in a cold sweat
- Nausea
What Causes a Widowmaker Heart Attack?
A widowmaker occurs when the left anterior descending artery (LAD), a major coronary artery that branches off the heart’s main blood supply, is completely blocked after a plaque rupture. Plaque in the LAD can be seen on a Coronary Calcium (CAC) scan, which is a helpful tool for monitoring the health of your arteries and risk for a widowmaker heart attack (and can provide a life-saving widowmaker calcium score).
The LAD artery supplies oxygenated blood to the interventricular septum between the left and right ventricles of the heart as well as the anterior left ventricle. The LAD artery can become subject to arterial plaque buildup, which can cause narrowing and stiffness in the artery. This progressive narrowing is a hallmark of coronary artery disease, the underlying condition that drives most widowmaker heart attacks.
Arterial plaque results from cholesterol, cellular waste, fatty substances, and fibers building up along the inner arterial wall. Eventually, due to inflammation, oxidation, stress, and weakening of the plaque structure, an arterial plaque can rupture and cause a blockage to the arteries, also known as coronary thrombosis.
Because the LAD artery is responsible for bringing oxygenated blood to half of the heart, a blockage can result in inadequate blood flow, myocardial injury, or damage to the heart muscle, and even disruptions in the heart’s normal contraction.
Understand Your Risk Factors
Despite its moniker of the “widowmaker,” a STEMI can affect anyone. Men are more likely to have a widowmaker heart attack than women, but the outcomes can differ greatly.
The American Heart Association recognizes several risk factors that can increase a person’s heart attack risk:
- Diabetes
- Hypertension
- Smoking
- Stress
- Weight
- Family history of coronary heart disease
- Dyslipidemia (an imbalance of cholesterol and/or triglycerides)
- Age — men aged 45 years and older and women aged 55 years and older are at higher risk
How to Prevent a Widowmaker Heart Attack
Whether you’re hoping to avoid an initial widowmaker heart attack or a recurrent one, prevention is essential. Optimizing your everyday lifestyle habits and utilizing preventive cardiovascular screens is key.
Preventive Screenings
Individuals who are at risk for heart disease between the ages of 40-70 years, and those with a family history of high cholesterol, can benefit from calcium-score screening. Regular screening can also help catch artery disease before it progresses to a medical emergency.
A CAC scan uses a CT scan to provide pictures of your heart’s arteries and calculates calcium deposits present in the heart. This includes a specific score for the LAD, so it does show how much hardened, calcified plaque has built up in that artery. A higher LAD calcium score indicates more plaque buildup and a greater risk for a widowmaker heart attack, since it reflects the exact artery involved.
Heart-Healthy Diet
Unfortunately, many individuals who have had a heart attack or are at an increased risk for one are prescribed a pretty generic “heart-healthy diet” with no personalized or detailed recommendations. Let’s unpack what this really means and why nutrition is so effective for improving heart health.

A great number of different food patterns, like a plant-based diet or Mediterranean diet, can be protective against a widowmaker heart attack. At the root of all things, a heart-healthy diet is one that is well-balanced in macronutrients, micronutrients, and therapeutic foods to help your heart work optimally.
Research shows that high-quality diets consisting of a variety of foods significantly reduce the risk of heart disease. Beyond providing vitamins, minerals, and macronutrients, various foods have compounds that give additional health benefits.
Key protective compounds include:
- Plant polyphenols — phytochemicals that can support healthy blood vessels, normal cholesterol levels, and protect against inflammation. Well-studied examples include resveratrol in black grapes, epigallocatechin gallate (EGCG) from tea, curcumin in turmeric, and quercetin in red onions.
- Plant sterols and stanols — plant substances structurally similar to cholesterol. They are effective for managing cholesterol levels due to their ability to inhibit cholesterol absorption in the body. However, in people who are hyperabsorbers of cholesterol, plant sterols can actually raise cholesterol instead of lowering it, so it’s worth testing for hyperabsorption before adding them.
- Phytoestrogens — like lignans and isoflavones from flaxseed and soy, which can protect women from cardiovascular disease. They have antioxidant and anti-inflammatory benefits, may help lower high cholesterol, improve endothelial health, and support hormonal balance.
- Fiber — found in plant foods, it supports healthy blood sugar regulation and increases insulin sensitivity. Insulin resistance increases your risk of type 2 diabetes, a major risk factor in cardiovascular disease. Eat a variety of fiber-rich foods like legumes, leafy greens, berries, cruciferous vegetables, and whole grains.
To get the most out of your diet, focus on adding in nutrient-rich therapeutic foods your body needs to achieve improved blood pressure control, reduced inflammation and oxidative stress, increased insulin sensitivity, and overall improved heart function.
Eating for heart health is a lifelong plan and should be sustainable for you. It’s important to work with a registered dietitian knowledgeable in cardiovascular health. I discuss all of these foods and how to balance them appropriately in my 6-week Heart Health Optimization group program.
Exercise
Regular exercise can support the flexibility of your arteries and reduce the risk of atherosclerosis. Current guidelines recommend that healthy adults get at least 150-300 minutes of moderate- to vigorous-intensity exercise weekly plus strength training twice a week.
Two types of exercise shown to be effective for heart health include:
- Aerobic (cardio) exercise — uses large muscle groups and is maintained for a while, including running, hiking, swimming, dancing, and biking.
- Resistance (strength) exercise — typically done for shorter durations and includes some weight resistance, such as weight lifting, squats and lunges, push-ups, and similar exercises.
Studies find that doing both resistance and aerobic exercise in your routine may be the most effective for losing weight, improving cardiorespiratory fitness, and increasing fat loss compared to resistance or aerobic exercise alone.
Medication
Taking medications as needed and as prescribed for normal blood clotting, blood pressure, and blood lipid levels can reduce the risk of further heart disease and complications. Never add, adjust, or stop medications without consulting with your provider.
It’s still important to monitor your labs regularly to make sure your medications are working well and being tolerated, and to catch when adjustments may be needed. Many of my clients have been able to reduce or eliminate medications with their physician’s guidance after implementing personalized, targeted, science-based nutrition.
Nutrition and medication management aren’t always enough on their own, though. In cases of severe or repeated blockage, a cardiologist may recommend procedures such as angioplasty or artery bypass surgery, also known as a coronary artery bypass graft (CABG), to restore blood flow to the heart.
Alongside any medical or procedural treatment, nutrition still plays a role in your recovery and ongoing prevention. If choosing to add supplements to your diet, you should always consult with your healthcare team, including your Registered Dietitian Nutritionist who specializes in heart disease, to ensure it’s personalized for you, is providing benefit versus potential harm, and takes into account your medical history, diet, and medications you use.
Monitoring Labs
Along with CAC scans, keeping up to date with your medical labs and blood tests can help you know when to seek additional support. Important labs to monitor during your regular doctor’s visits include:
- Blood pressure
- hsCRP
- apoB or if not available, non-HDL cholesterol
- Triglycerides
- Hemoglobin A1c
- LP-IR for insulin resistance
I created a self-paced course to help you learn more about the other lab tests and risk-based targets that may help you better assess your heart health.
Weight Management
Managing your weight can reduce your risk of heart attack and other chronic conditions that can cause damage to your vascular system. People with a BMI of 25 or higher generally have a greater risk of getting a widowmaker heart attack. Losing 5-10% of your body weight can significantly reduce certain cardiovascular risks like triglyceride levels, LDL, and total cholesterol.
Not all weight loss diets are heart healthy, though. Trendy or overly restrictive diets can lead to weight loss without actually protecting your heart, and some can even work against your cardiovascular health. I work with my clients to target visceral fat specifically, using a heart-healthy approach that supports your labs and vascular health as the weight comes off.
In addition to managing your overall weight, where your weight settles has an impact on your cardiovascular risk. Waist circumference is an anthropometric measurement that correlates with visceral adiposity, or fat that surrounds the internal organs. A higher waist circumference is associated with a greater risk of metabolic disease because this type of fat is more metabolically active and is usually associated with inflammation and insulin resistance.
Current guidelines note that a waist circumference greater than 102 cm (40 in) in men or 88 cm (35 in) in women is associated with greater health risks. However, these guidelines are not universal, and waist circumference thresholds may differ based on BMI category and ethnicity. For South Asian populations specifically, these thresholds tend to be lower, since metabolic syndrome and cardiovascular risk can appear at a lower BMI and lower waist circumference than in other populations.
Waist-to-hip ratio is another useful measurement, with elevated risk starting above 0.85 in women and 0.90 in men. When measuring waist circumference, measure around your belly button, not at your pants size, since pants sizing is a common mistake that can under- or overestimate your actual risk.
Smoking Cessation
Smoking is a major risk for the development of arterial plaques and heart attacks. Smoking damages the blood vessels, decreases blood flow and oxygen delivery to the heart, and increases inflammation, which can promote plaque formation.
Research shows that female smokers have a 25% higher risk of developing coronary heart disease than men with the same exposure to tobacco smoke. Fortunately, smoking cessation is one of the most impactful things you can do to protect your heart health and lower your risk of a heart attack.
Diabetes Management
Diabetes is a risk factor for heart attacks due to its impact on the health of your vascular system. Excess blood glucose can decrease the elasticity of your blood vessels, reduce blood flow, and increase high blood pressure risk.
Insulin resistance plays a role too, even before diabetes develops. It can reduce your body’s ability to clear LDL particles from the blood, allowing them to linger and contribute to plaque buildup.
Managing your blood sugar through diet, exercise, and prescribed medications as needed can minimize the damage to the blood vessels and arteries of your heart.
What is a Widowmaker Heart Attack: FAQs
Can a person survive a widowmaker heart attack?
Yes, a person can survive a widowmaker heart attack. The name sounds frightening, but survival is very possible, especially with prompt medical care. The 30-day mortality rate for a widowmaker heart attack ranges from 2.5% to 10%, meaning the majority of people who receive fast treatment do survive. With today’s emergency treatment options and strong prevention strategies, a widowmaker heart attack doesn’t have to live up to its name.
What is the widowmaker heart attack?
A widowmaker heart attack is the common name for an anterior ST-segment elevation myocardial infarction (STEMI), a severe type of heart attack caused by a near-complete or complete blockage of the left anterior descending (LAD) artery. It earned its intimidating nickname because this artery supplies oxygenated blood to a large portion of the heart, making a blockage here especially dangerous without immediate treatment. That name reflects how serious this event can be, but it doesn’t reflect what’s possible today. With fast intervention and proactive prevention, many people go on to fully recover.
Are there warning signs with widowmaker?
Yes, but the real warning signs happen long before any physical symptoms show up. A widowmaker heart attack develops from plaque buildup in the LAD artery over time, and that process leaves early clues in your labs. Rising inflammation, atherogenic cholesterol particles like ApoB or LDL-P, and endothelial dysfunction can all signal that plaque is forming, often years before you’d feel anything.
This is why routine bloodwork and screenings like a CAC scan matter so much. Catching these warning signs early gives you the opportunity to intervene with targeted, science-based nutrition before a blockage ever develops. Physical symptoms like chest pain or shortness of breath tend to show up only once a heart attack is already happening, which is a different stage than the early warning signs described here.
What’s the difference between a widowmaker and a regular heart attack?
The main difference between a widowmaker and a regular heart attack is the location and severity of the blockage. A widowmaker specifically involves a near-complete or complete blockage of the left anterior descending (LAD) artery, which supplies blood to a large portion of the heart, including the interventricular septum and the anterior left ventricle. Other heart attacks may involve smaller arteries or partial blockages, which generally affect less heart tissue. The widowmaker name reflects the size of the artery involved, not a guaranteed outcome. Prognosis still comes down to how quickly it’s treated and how proactively future risk is managed afterward.
What are widow maker heart attack symptoms?
Widow maker heart attack symptoms include pain or discomfort in the neck, jaw, back, arms, or stomach, shortness of breath, chest pain, tightness, or discomfort, lightheadedness, weakness, or feeling faint, breaking out in a cold sweat, and nausea. These symptoms can appear suddenly and should always be treated as a medical emergency, since acting quickly is one of the biggest factors in a full recovery.
What does a widowmaker heart attack feel like?
A widowmaker heart attack often feels like tightness, pressure, or discomfort in the chest, which may spread to the neck, jaw, back, arms, or stomach. Many people also experience shortness of breath, a cold sweat, nausea, and lightheadedness or weakness. Because the LAD artery supplies blood to such a large portion of the heart, these symptoms can feel intense, but recognizing them quickly and getting emergency care gives you the best chance at a strong recovery.
What is a widowmaker heart attack survival rate?
The widowmaker heart attack survival rate corresponds to a 30-day mortality rate of 2.5% to 10%, meaning most people survive when they receive prompt treatment. Mortality rates are slightly higher in women than in men. While the name widowmaker suggests near-certain fatality, that isn’t the reality for most people today. Getting to emergency care quickly, along with focused prevention afterward, can meaningfully change what this diagnosis means for your future.
What is a widow maker heart attack ECG?
A widowmaker heart attack shows up on an ECG as ST-segment elevation, which is the defining feature of a STEMI. Because a widowmaker specifically involves the left anterior descending (LAD) artery, this ST-segment elevation typically appears in the leads that correspond to the front, or anterior wall, of the heart. This distinct pattern allows doctors to identify a widowmaker heart attack quickly and begin treatment right away, which is a major reason survival outcomes have improved.
What is the widowmaker artery?
The widowmaker artery is the left anterior descending (LAD) artery, the main vessel that supplies oxygenated blood to the interventricular septum and the anterior wall of the left ventricle. It earns the ominous nickname because a severe blockage here, caused by a ruptured plaque, cuts off blood flow to such a large portion of the heart. But an intimidating name doesn’t mean an inevitable outcome. With advances in emergency cardiac care and evidence-based prevention strategies, a blockage in this artery no longer has to be as fatal as its name implies.
What is life after a widowmaker heart attack like?
Life after a widowmaker heart attack can look very different depending on how quickly you got treatment and how you approach recovery afterward. Many people need to adjust their diet, exercise routine, and medications, and some also work through the emotional impact of a life-threatening cardiac event. One of my clients had a widowmaker heart attack at age 40 with an ejection fraction of 30%, indicating heart failure. Within 3 months of personalized nutrition support, his ejection fraction rose to 47%, and within a year it reached 61%, allowing him to come off his beta blocker and statin. Life after a widowmaker heart attack can mean a stronger heart than before with the right support.
Widowmaker Heart Attack: Final Thoughts
While a widowmaker heart attack is very dangerous, there are many things you can do to help lower your risk of ever experiencing one. Never underestimate the power that science-based nutrition and optimized lifestyle habits can have on your cardiovascular health, no matter what they look like today. It’s never too late to make these changes, especially if you’re concerned about your risk factors.
As a cardiovascular dietitian, I’m ready to help you come up with a personalized plan to protect your heart health. Click here to schedule a discovery call with me to talk through our options for working together.
About the Author
Michelle Routhenstein, MS, RD, CDE is a Cardiology Dietitian and Preventive Cardiology Nutritionist with over 14 years of experience helping people take control of their heart health. She graduated cum laude from New York University with both a Bachelor of Science and Master of Science in Nutrition and Dietetics, and has worked in clinical settings including a level-one trauma hospital in NYC.
As the owner of Entirely Nourished, Michelle has helped thousands of individuals lower their blood pressure and cholesterol, reduce their risk of heart attacks and strokes, and in many cases reduce or eliminate heart medications entirely through her science-based, personalized approach to nutrition. She specializes in helping women understand and address the deeper drivers of cardiovascular risk, including those that surface during and after pregnancy.
If you’re ready to take a proactive approach to your heart health, you can work with Michelle through individual nutrition counseling or inside her 6-week group program, Optimize, designed to give you clarity, confidence, and real results.
References
- Akbar H, Foth C, Kahloon RA, et al. Acute ST-Elevation Myocardial Infarction. StatPearls Publishing; 2024. Link
- Cenko E, Yoon J, Kedev S, et al. Sex Differences in Outcomes After STEMI. JAMA Intern Med. 2018;178(5):632-639. doi:10.1001/jamainternmed.2018.0514
- American Heart Association. Warning Signs of a Heart Attack. 2022.
- Palasubramaniam J, Wang X, Peter K. Myocardial Infarction-From Atherosclerosis to Thrombosis. Arterioscler Thromb Vasc Biol. 2019;39(8):e176-e185. doi:10.1161/ATVBAHA.119.312578
- American Heart Association. Understand Your Risks to Prevent a Heart Attack. 2022.
- Petersen KS, Kris-Etherton PM. Diet Quality Assessment and the Relationship between Diet Quality and Cardiovascular Disease Risk. Nutrients. 2021;13(12):4305. doi:10.3390/nu13124305
- Khurana S, Venkataraman K, Hollingsworth A, Piche M, Tai TC. Polyphenols: Benefits to the Cardiovascular System in Health and in Aging. Nutrients. 2013;5(10):3779-3827. doi:10.3390/nu5103779
- Trautwein EA, Vermeer MA, Hiemstra H, Ras RT. LDL-Cholesterol Lowering of Plant Sterols and Stanols. Nutrients. 2018;10(9):1262. doi:10.3390/nu10091262
- Rietjens IMCM, Louisse J, Beekmann K. The Potential Health Effects of Dietary Phytoestrogens. Br J Pharmacol. 2017;174(11):1263-1280. doi:10.1111/bph.13622
- Yang YJ. An Overview of Current Physical Activity Recommendations in Primary Care. Korean J Fam Med. 2019;40(3):135-142. doi:10.4082/kjfm.19.0038
- Patel H, Alkhawam H, Madanieh R, Shah N, Kosmas CE, Vittorio TJ. Aerobic vs Anaerobic Exercise Training Effects on the Cardiovascular System. World J Cardiol. 2017;9(2):134-138. doi:10.4330/wjc.v9.i2.134
- Schroeder EC, Franke WD, Sharp RL, Lee DC. Comparative Effectiveness of Aerobic, Resistance, and Combined Training on Cardiovascular Disease Risk Factors. PLoS One. 2019;14(1):e0210292. doi:10.1371/journal.pone.0210292
- Brown JD, Buscemi J, Milsom V, Malcolm R, O’Neil PM. Effects on Cardiovascular Risk Factors of Weight Losses Limited to 5-10%. Transl Behav Med. 2016;6(3):339-346. doi:10.1007/s13142-015-0353-9
- Ross R, Neeland IJ, Yamashita S, et al. Waist Circumference as a Vital Sign in Clinical Practice. Nat Rev Endocrinol. 2020;16(3):177-189. doi:10.1038/s41574-019-0310-7
- Gallucci G, Tartarone A, Lerose R, Lalinga AV, Capobianco AM. Cardiovascular Risk of Smoking and Benefits of Smoking Cessation. J Thorac Dis. 2020;12(7):3866-3876. doi:10.21037/jtd.2020.02.47
